

Periprosthetic fracture
A periprosthetic fracture A hip or knee is a fracture of the bone located around or near a prosthesis, most often a hip or knee prosthesis. It can occur after a fall or trauma, and sometimes after a moderate impact when the bone is weakened.
Treatment depends on the location and displacement of the fracture, as well as the stability of the prosthesis. If the implant remains well-fixed, the surgeon can sometimes stabilize the bone by preserving it. If a component is loose or does not provide satisfactory fixation, a revision of the prosthesis may be considered.
A periprosthetic fracture does not automatically lead to the same treatment. Clinical examination and imaging help determine whether to monitor and protect weight-bearing, surgical fixation, or prosthetic revision, sometimes in combination.
UNDERSTANDING A FRACTURE OF THE FEMORAL NECK

RECOGNIZING THE SIGNS OF A PERIPROSTHETIC FRACTURE
A periprosthetic fracture It can cause sudden pain near the prosthesis, in the hip, thigh, or knee, depending on its location. The pain may prevent weight-bearing or normal movement of the limb.
- Pain after a fall or impact: It can appear around the hip, thigh, or knee.
- Difficulty or impossibility of gaining support: Walking becomes painful, unsteady, or impossible.
- Swelling or bruising: They may appear near the fractured area, but their absence does not rule out a fracture.
- Change in mobility or feeling of instability: The limb may be difficult to move or seem less stable than before.
After an injury near a prosthesis, significant pain or the inability to bear weight warrants prompt medical evaluation. Avoid forcing yourself to walk or moving the affected limb.
WHY DOES A PERIPROSTHETIC FRACTURE OCCUR?
A periprosthetic fracture occurs when stress exceeds the strength of the bone surrounding a prosthesis. The cause, bone quality, condition of the prosthesis, and circumstances of the trauma are taken into account to understand the situation and plan treatment.
FALL OR TRAUMA
A fall on one's side or a direct impact can cause a fracture near a hip or knee prosthesis. More severe trauma can result in a more complex fracture.
BONE FRAGILITY
Osteoporosis or reduced bone quality can make bones more vulnerable. A fall from a low height can then be enough to cause a fracture.
PROSTHESIS STABILITY
Fixing the prosthesis to the bone is an essential element of the assessment. A loose component can alter the choice of treatment and lead to consideration of a revision.
CONDITION OF THE BONE AROUND THE IMPLANT
The quantity and quality of available bone influence the possibilities for fixation. The surgeon also takes into account any previous fractures or surgeries and the type of prosthesis.
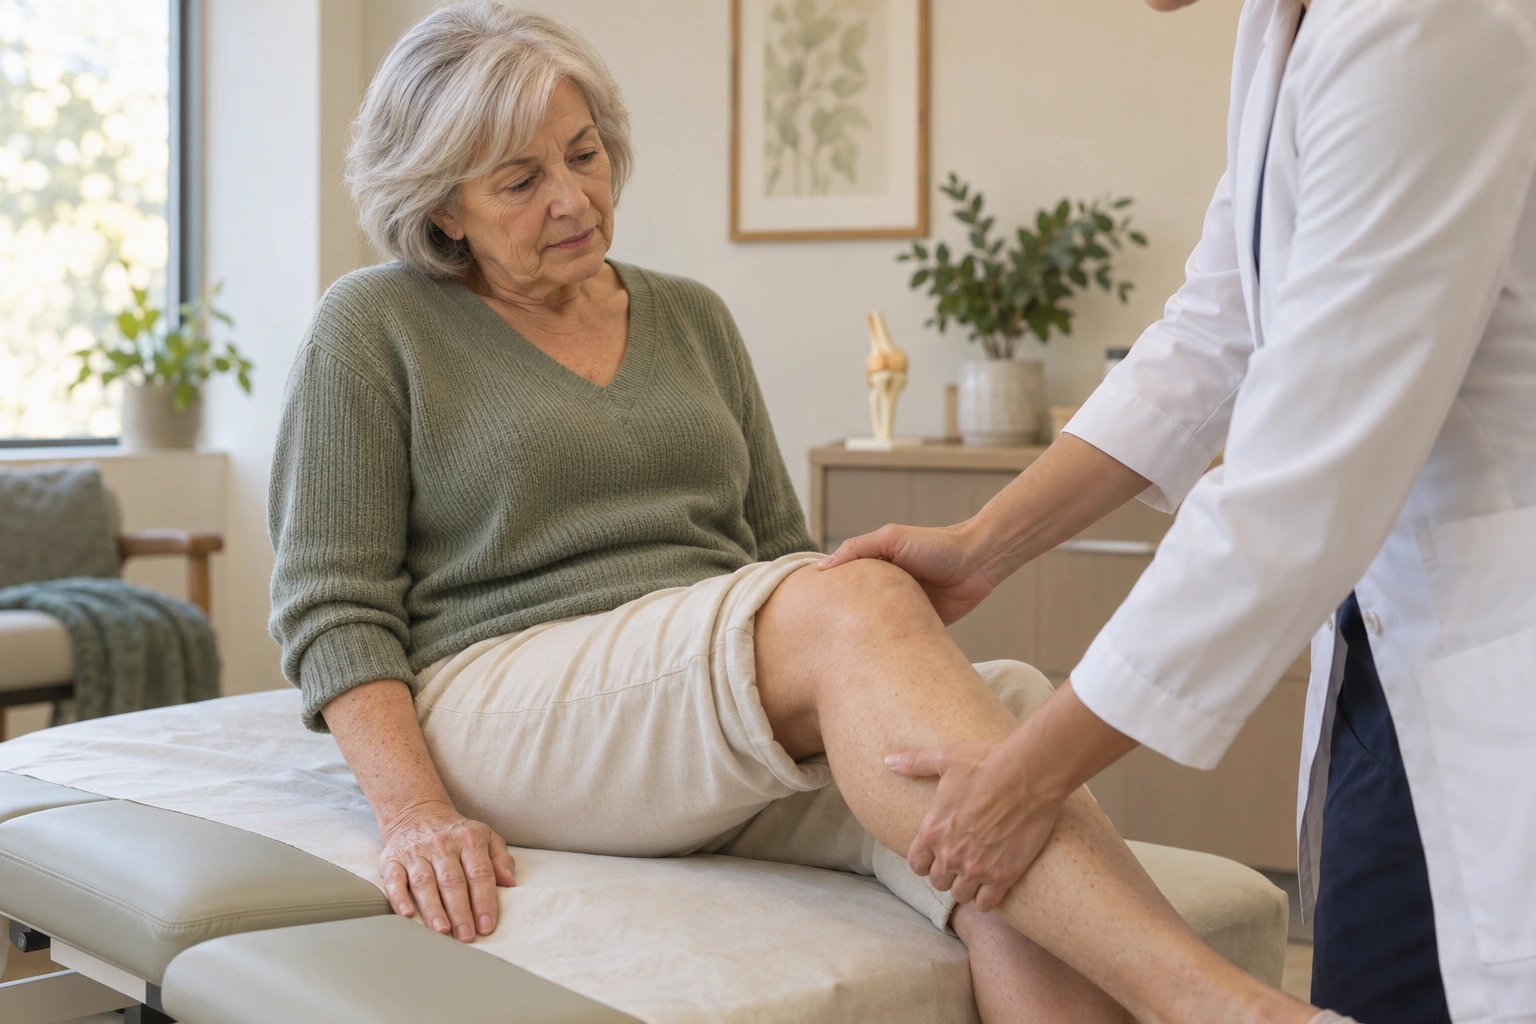
MAKE THE RIGHT DIAGNOSIS
Diagnosis is based on clinical examination and imaging. X-rays usually allow the fracture to be located and the prosthesis to be observed. Depending on the results, a CT scan or other examinations may be ordered to further define the fracture and plan treatment.
01 — THE CLINICAL EXAMINATION
The doctor assesses pain, mobility, weight-bearing capacity, and skin condition. Sensation, movement, and circulation in the limb are also checked.
02 — X-RAYS
X-rays show the location of the fracture and help assess the displacement as well as the position of the prosthesis. Previous images, when available, can help compare the condition of the implant.
03 — THE SCAN AND THE PRE-OPERATIVE ASSESSMENT
A scan can determine the shape of the fracture and the relationship between the bone and the prosthesis. If surgery is being considered, the assessment also includes an evaluation of the patient's general condition and a consultation with an anesthesiologist.
Treatment depends on the fracture, but also on the stability of the prosthesis: these two elements must be evaluated together.
TREAT THE FRACTURE AND STABILIZE THE BONE
The management of a periprosthetic fracture The outcome depends on the degree of displacement, the stability of the implant, and the quality of the bone. In selected cases, weight-bearing protection and specialized monitoring may be considered. Surgery may be recommended to stabilize the fracture or replace an unstable prosthetic component.
PROTECT THE AREA AND RELIEVE THE PAIN
The team chooses a comfortable position and specifies whether weight-bearing should be avoided or limited. Pain is managed and the patient's overall condition is monitored. Movement instructions are tailored to the fracture and the prosthesis in question.
FIX THE FRACTURE WHILE KEEPING THE PROSTHESIS
If the prosthesis is stable and the fracture can be fixed around it, the surgeon can use a plate, screws, or cables. The method of fixation is chosen based on the location of the fracture, the available bone, and the presence of the prosthetic stem.
REVISING AN UNSTABLE COMPONENT
If a component becomes loose or fails to provide adequate stabilization, a revision of the prosthesis may be considered. The component replaced and the method of fixation depend on the available bone and the nature of the fracture.
COMBINING FIXING AND REVISION
Some fractures require both component replacement and bone fixation. The choice of this strategy depends on the desired stability and the feasibility of obtaining a suitable fixation.
The strategy aims to stabilize the bone while taking into account the prosthesis and the patient's recovery capacity.Treatment can therefore vary from one fracture to another, even when the symptoms are similar.

WHEN TO CONSIDER SURGERY?
Surgery may be considered if the fracture is displaced or unstable, if the prosthesis is loose, or if reliable stabilization cannot be achieved without intervention. Some minimally displaced fractures, with a stable prosthesis and a compatible clinical situation, can sometimes be monitored with appropriate guidelines.
IF THE FRACTURE IS DISPLACED OR UNSTABLE
Surgical fixation may be offered to hold the fragments in place and promote consolidation in a satisfactory position.
IF THE PROSTHESIS IS LOOSE
An unstable component may require revision. The surgeon assesses whether this revision should be combined with fracture fixation.
DEPENDING ON THE PATIENT'S GENERAL CONDITION AND OBJECTIVES
The decision takes into account pain, autonomy, the possibility of weight-bearing, the patient's general condition, and the risks associated with the procedure. The operation is not decided based on a single image.
REHABILITATION AND RESUMPTION OF ACTIVITIES
Recovery depends on the fracture, the fixation performed, the stability of the prosthesis, and the patient's overall condition. Rehabilitation begins when the team determines that movement and weight-bearing are compatible with the treatment plan.
01 — GETTING BACK IN MOTION SAFELY
Initial transfers and movements are accompanied by the team. Walking aids, such as crutches or a walker, may be necessary.
02 — FOLLOW THE SUPPORT INSTRUCTIONS
Weight-bearing may be permitted, limited, or delayed depending on the fracture and the stability achieved. Instructions are given by the surgeon and reassessed at follow-up appointments.
03 — REGAIN MOBILITY AND STRENGTH
Rehabilitation can work on mobility, muscle strengthening, balance, and gait. The exercises are adapted to the treated area and the patient's progress.
04 — RESUME DAILY ACTIVITIES
Movement within the home, stairs and daily activities gradually resume, depending on autonomy, pain and walking safety.
05 — ADAPTING THE RETURN TO WORK AND SPORT
The return to work depends on consolidation, functional capacity, the nature of the work or sport, and medical validation.
The rate of recovery is individual and follows the evolution of the fracture and the prosthesis.


A CARE APPROACH TAILORED TO EACH PATIENT
A periprosthetic fracture is not treated solely based on its location. A similar fracture may require fixation, prosthesis revision, or another strategy depending on implant stability and bone quality.
Treatment is chosen taking into account age, anatomy, general condition, independence, type of prosthesis, fracture, and previous treatments. The possibility of weight-bearing and personal goals are also factors in the decision.
The technique, support instructions and recovery program are adapted to the situation and reassessed during follow-up.
«"The choice of treatment is based on a joint analysis of the fracture, the prosthesis, and the patient's overall condition."»
Minimally invasive surgery can refer to several methods of accessing the joint and visualization techniques. It is not a single technique applicable to all knee and hip pathologies.
The choice depends on the structure to be treated, the extent of the procedure, and the functional objectives. Arthroscopy is one of the minimally invasive techniques used to explore or treat the inside of a joint.
FREQUENTLY ASKED QUESTIONS
DO YOU WANT TO BETTER UNDERSTAND YOUR FRACTURE?
A consultation allows for the assessment of the fracture, the stability of the prosthesis, and the treatment options. The clinical examination and imaging analysis help to discuss the strategy best suited to your situation.
